Thursday, October 1, 2026
Clear, 69°Wind: mph,

Welcome to our new web site!
To give our readers a chance to experience all that our new website has to offer, we have made all content freely avaiable, through October 1, 2018.
During this time, print and digital subscribers will not need to log in to view our stories or e-editions.

In September 2026, the FDA held its first-ever public workshop on testosterone use in menopausal women. The questions on the table: What can testosterone actually do for women? How can they use it safely? And what will it take to develop standardized treatments designed for their bodies?
Testosterone is not currently FDA-approved for women, although doctors increasingly prescribe it off-label, with prescriptions to women nearly tripling from 2016 to 2025.
FDA workshop experts agreed that the evidence for testosterone in women is strongest for treating low sexual desire, known as hypoactive sexual desire disorder, or HSDD. Benefits for energy, mood, memory, and muscle, they said, need more study.
But in an analysis of more than 1,220 women in perimenopause or menopause from physician-led longevity platform Hone Health, women who took testosterone reported meaningful improvements across 18 menopause symptoms, with the biggest gains in sexual desire, energy, strength, and stamina.
In September 2026, Hone analyzed menopause symptom improvement in 1,220 women taking testosterone but not estrogen or progesterone menopause hormone therapy. Symptoms were ranked using a standard questionnaire that healthcare providers use to track how menopause affects daily life.
The biggest improvements for women taking testosterone fell into three categories: sexual health, energy and stamina, and physical improvements such as muscle mass.
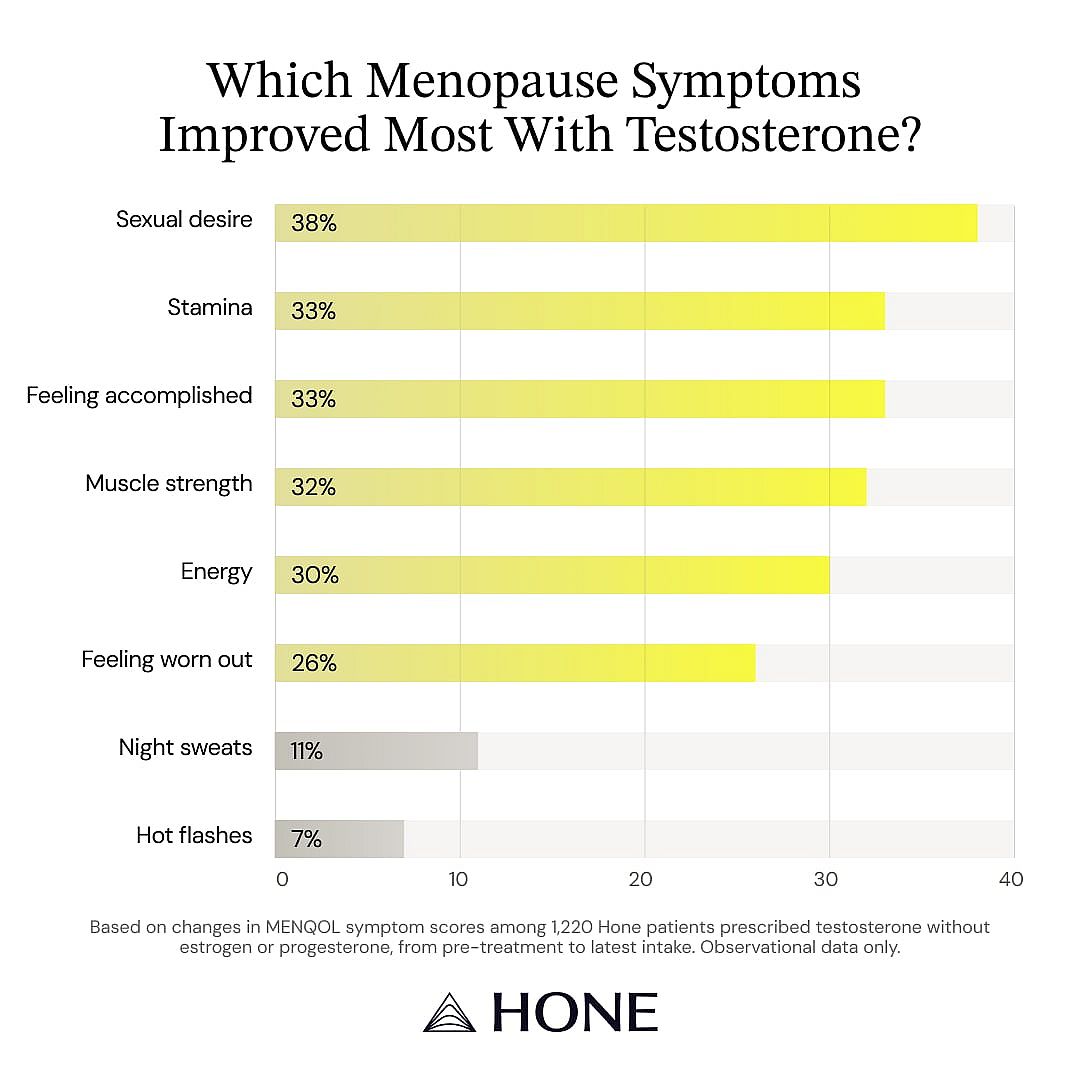
These improvements suggest that testosterone drives gains in energy, desire, and vitality in menopausal women.
"Much of this doesn't surprise me because it lines up with what we know testosterone is doing in the body," says Dr. Natalie Kunsman, MD, a Hone-affiliated family doctor who specializes in hormone health and regenerative medicine. “Tracking specific symptoms is like looking through a keyhole when we know testosterone is working the whole room."
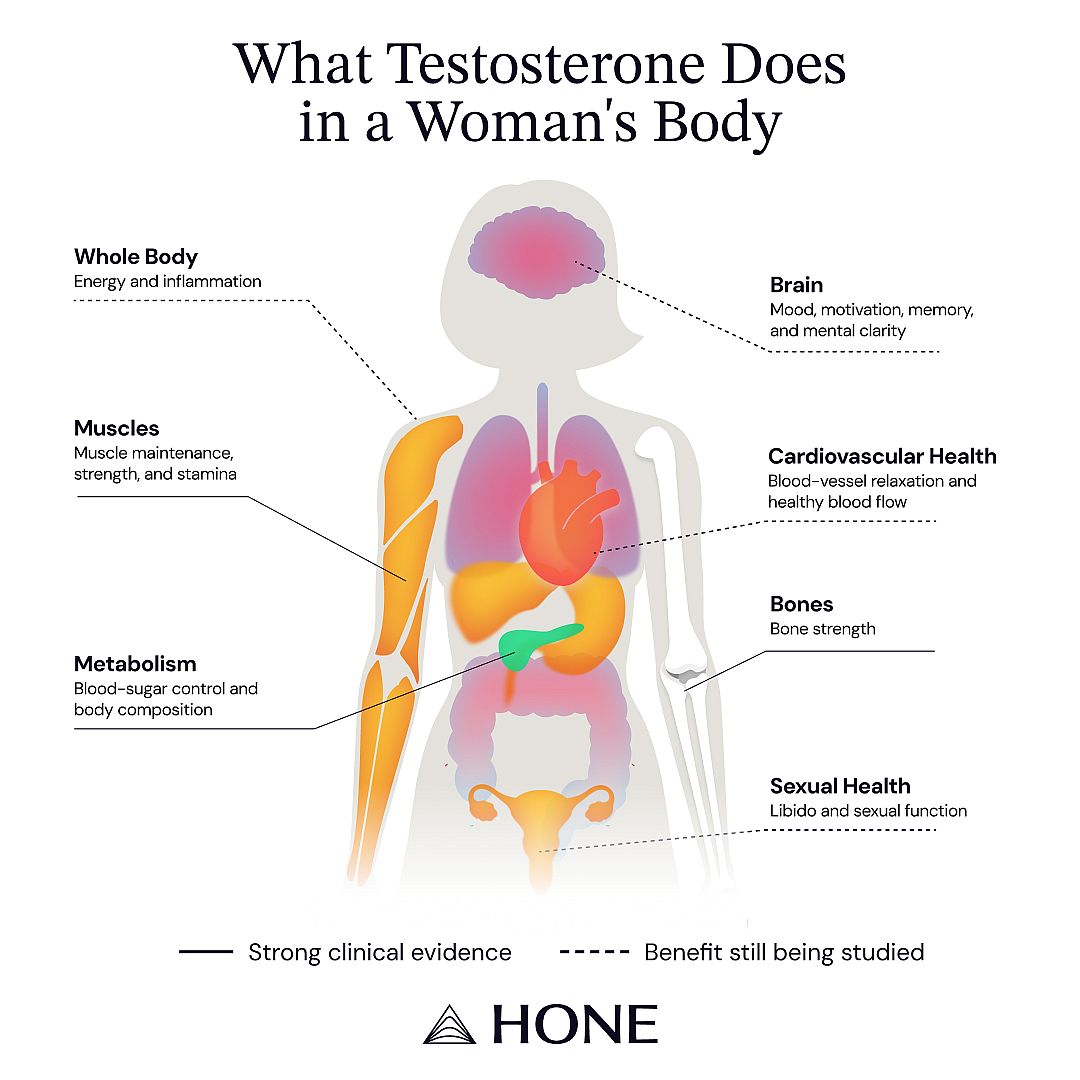
Doctors affiliated with Hone Health say testosterone’s benefits can extend well beyond sexual health. That makes sense given that testosterone receptors sit across multiple systems in the female body: throughout the brain, muscles, bones, and cardiovascular system. Women’s testosterone levels gradually decline with age, although the drop isn’t as closely tied to menopause as the declines in estrogen and progesterone.
Kunsman emphasizes that testosterone’s benefits for women don't always show up in symptom scores, but research increasingly backs them:
Kunsman believes testosterone should be part of the HRT conversation alongside estrogen and progesterone. "Just because we don't have testicles doesn't mean we don't need testosterone," she says. The aim is physiological dosing that restores a woman to a range that’s optimal for her age and life stage.
If you're dealing with low sexual desire, low energy, loss of strength, or weight gain, especially in perimenopause or postmenopause, talk to your doctor about your symptoms. These questions can help guide the conversation:
If your physician isn't open to prescribing testosterone within the normal female range, telehealth companies offer physician-guided testosterone therapy for women as part of a hormonal assessment that includes lab work and regular follow-up appointments.
Results come from Hone Health patient data in the Women's Optimization category, as of September 2026. Symptom outcomes were measured using the Menopause Quality of Life Questionnaire (MENQOL), a validated clinical tool that scores symptoms from 0 to 6, where lower scores mean fewer or less bothersome symptoms. In men, physicians use the qADAM questionnaire to assess testosterone deficiency, but there is no equivalent for women.
The analysis compared each patient's first and most recent MENQOL assessment. Women with fewer than two assessments were excluded. The test group included 1,220 patients who had a testosterone prescription and no recorded estradiol, estrogen, or progesterone prescription through Hone.
These are observational findings with no randomized control group, so they show association, not proof of cause and effect. Prescription records reflect Hone history only. Some patients may have received hormones from other providers not captured in this data.
This story was produced by Hone Health and reviewed and distributed by Stacker.


